


Article by
Peterson Huang DMD, MS, FACP, FRCDC
Dr. Peterson Huang is a dual board-certified prosthodontist serving Falls Church and Northern Virginia. He has been recognized as a Top Prosthodontist by Northern Virginia Magazine and Arlington Magazine and is affiliated with the Inova Fairfax Hospital Tumor Board. Dr. Huang focuses on dental implants, full mouth reconstruction, and complex restorative dentistry for patients who need advanced, comprehensive care.
Full-mouth rehabilitation requires far more than restoring individual damaged teeth; it involves re-establishing an entire stomatognathic system in which the muscles, temporomandibular joints (TMJs), periodontium, and dental arches function in equilibrium. At the heart of this comprehensive restorative process is vertical dimension management—the precise diagnostic planning and clinical execution required to evaluate, modify, or restore the vertical height of a patient's bite.
Whether a patient presents with severe wear from decades of bruxism, extensive acid erosion, or posterior bite collapse due to missing teeth, altering the bite is an advanced clinical undertaking. Because vertical dimension is not an arbitrary number or a single universal standard, success depends entirely on methodical diagnostic sequencing, objective physiological markers, and patient-specific adaptation. At Nova Premier Dental in Falls Church, Virginia, complex restorative rehabilitation is guided by rigorous prosthodontic principles designed to deliver structural stability, masticatory efficiency, and balanced facial aesthetics.
What Is Vertical Dimension of Occlusion (VDO) and Why Does It Matter?
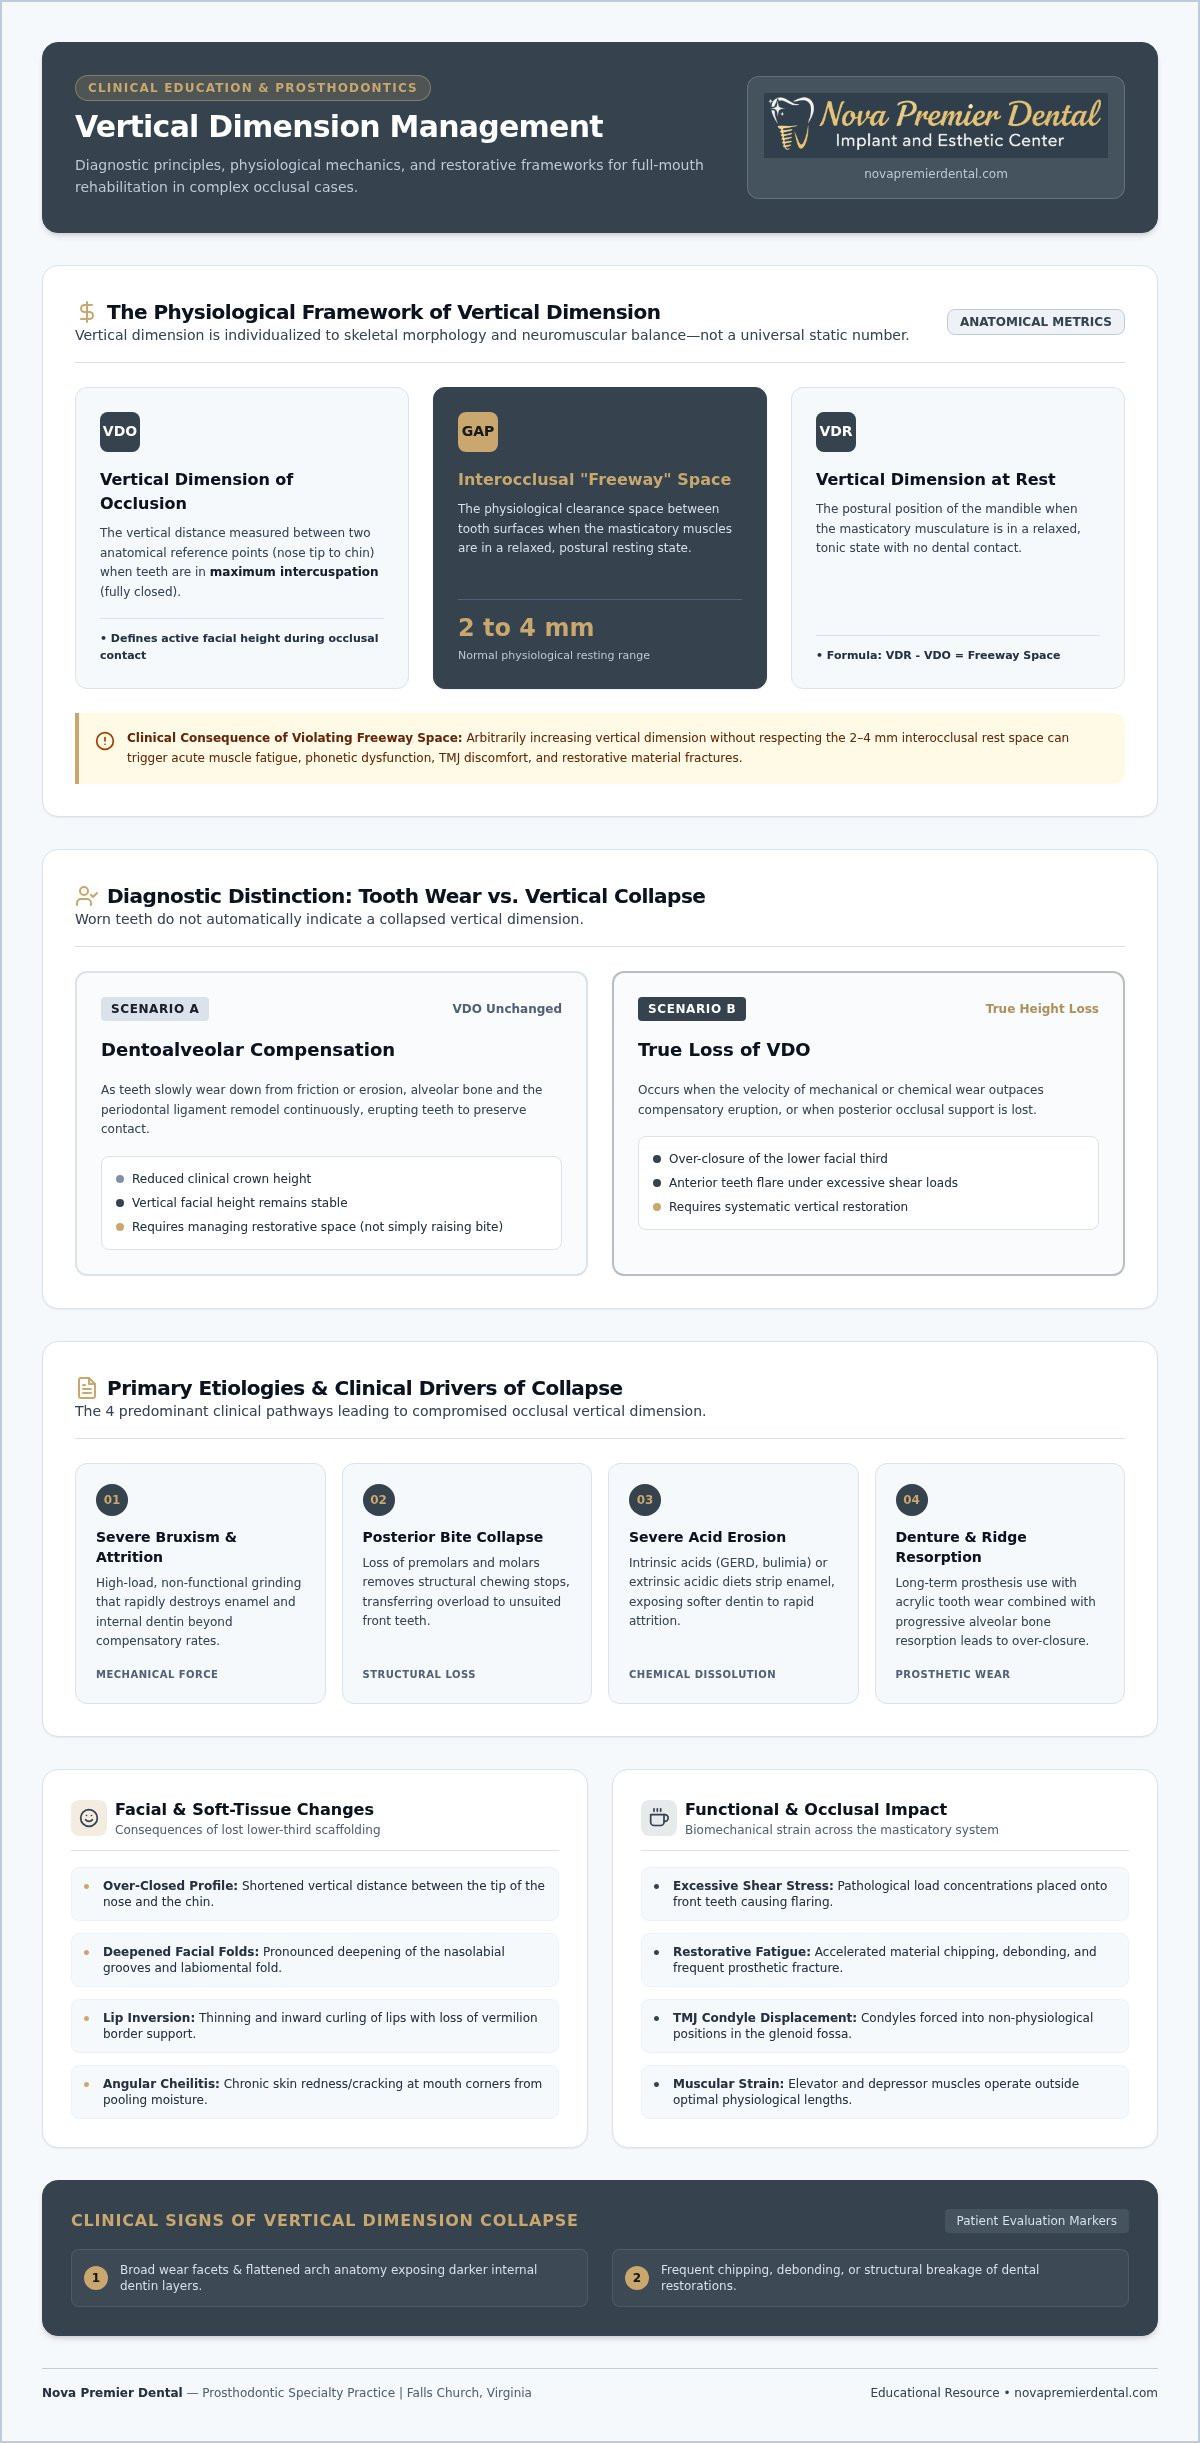
The Vertical Dimension of Occlusion (VDO) is defined as the vertical distance measured between two selected anatomical points—typically one on the tip of the nose and one on the chin—when the upper and lower teeth are in maximum intercuspation (fully closed together). It defines the physiological height of the lower third of the face during active contact.
In contrast, Vertical Dimension at Rest (VDR) represents the postural position of the mandible when the masticatory musculature is in a relaxed, tonic state and the teeth are not in contact. The difference between these two measurements is known as the interocclusal rest space or "freeway space," which typically ranges between two and four millimeters in a healthy dentition. This freeway space provides the necessary clearance for speech articulation and muscular relief; violating it by arbitrarily increasing vertical height can result in muscle fatigue, joint discomfort, phonetic problems, and restorative fracture.
Crucially, vertical dimension is individualized rather than a single universal standard. There is no predetermined millimeter measurement that applies to every individual. Instead, a patient’s optimal VDO exists within a physiological range governed by their unique skeletal morphology, neuromuscular balance, joint stability, and remaining hard tissue architecture. Sound vertical dimension management seeks to find this specific, comfortable baseline rather than forcing the patient into an idealized template.
The Role of Vertical Dimension in Facial Harmony
The teeth and alveolar ridges provide the structural scaffolding for the lower third of the face. When the vertical dimension diminishes, the soft tissues lose their underlying support. This anatomical change frequently results in:
- A noticeable shortening of the distance between the nose and chin, producing an over-closed profile.
- Deepening of the nasolabial grooves and the labiomental fold.
- Inversion and thinning of the lips (loss of the vermilion border).
- The development of angular cheilitis (chronic redness or cracking at the corners of the mouth) due to chronic moisture pooling in deepened skin folds.
By systematically restoring the correct vertical dimension, a prosthodontist provides renewed support to the perioral musculature, smoothing deep folds and restoring natural lower-facial proportions without surgical intervention.
Functional Occlusion and Biomechanical Stability
Beyond appearance, VDO dictates the biomechanical distribution of forces across the masticatory system. An unstable or collapsed vertical dimension places excessive shear stress on anterior teeth, accelerates mechanical fatigue on dental restorations, and forces the condyles of the TMJ into non-physiological positions within the glenoid fossa. Proper management stabilizes the relationship between the jaws, allowing the elevator and depressor muscles to function within their optimal resting lengths and minimizing pathological strain.
The Clinical Drivers of Vertical Dimension Loss
A common misconception is that worn teeth automatically mean a collapsed vertical dimension. In clinical prosthodontics, diagnosing a true loss of VDO requires distinguishing between tooth structure loss and true vertical height loss.
The human body possesses a remarkable adaptive mechanism known as dentoalveolar compensation. As teeth slowly wear away over years due to mechanical friction (attrition) or chemical dissolution (erosion), the alveolar bone and periodontal ligament often remodel, erupting the teeth continuously to maintain occlusal contact. In these scenarios, the patient may have lost substantial clinical crown height, but their VDO remains essentially unchanged. Restoring these teeth requires managing available restorative space, rather than simply raising the bite across the board.
True loss of VDO occurs when the rate of wear outpaces compensatory eruption, or when structural support is abruptly removed. Common etiologies include:
- Severe Attrition and Bruxism: High-load, non-functional parafunctional grinding that rapidly destroys enamel and dentin.
- Posterior Bite Collapse: The loss of premolars and molars removes the posterior stops that bear the bulk of chewing forces. The remaining front teeth, unsuited for axial masticatory loads, flare outward or wear down rapidly, causing the jaw to close further than normal.
- Severe Intrinsic or Extrinsic Acid Erosion: Gastroesophageal reflux disease (GERD), bulimia, or heavy consumption of acidic beverages can strip enamel, leaving softer dentin exposed to rapid mechanical destruction.
- Denture Wear and Residual Ridge Resorption: Long-term wearers of complete or partial prostheses often experience severe alveolar bone resorption alongside acrylic tooth wear, leading to progressive mandibular over-closure.
Signs You May Have Lost Vertical Dimension
Patients experiencing true vertical collapse often exhibit recognizable clinical signs, including:
- Visual flattening or broad wear facets across the entire arch, exposing darker internal dentin.
- Frequent chipping, debonding, or breakage of restorations such as crowns, fillings, or partials.
- Fatigue in the masseter and temporalis muscles during chewing.
- Difficulty articulating sibilant sounds ("S" sounds), often sounding like a whistle or lisp due to altered air pathways.
- Restricted clearance between the upper and lower teeth when attempting to place standard crowns.
Diagnostic Evaluation: Establishing the Prosthodontic Blueprint
Altering the vertical dimension is irreversible once definitive preparations begin. Therefore, the diagnostic phase must be comprehensive, precise, and completely verifiable before any restorative instrument touches a tooth. Thorough occlusal analysis and bite care forms the bedrock of treatment planning.
Treatment begins with an exhaustive collection of diagnostic records, including high-resolution photographic series, digital intraoral scans, low-dose cone-beam computed tomography (CBCT) to evaluate bone volume and condylar anatomy, and facebow transfers. The facebow records the spatial relationship of the maxillary arch to the patient's transverse horizontal axis (hinge axis) of the TMJ, transferring this accurate orientation to a semi-adjustable or fully adjustable articulator.
Establishing Centric Relation
When vertical dimension has collapsed or multiple teeth are severely worn, the patient's existing maximum intercuspation (habitual bite) is rarely a reliable reference point. Instead, prosthodontists reference Centric Relation (CR)—an orthopedically stable, repeatable position of the mandible where the condyles articulate in the anterior-superior position against the posterior slopes of the articular eminences, independent of tooth contact.
To capture this position accurately, muscle hyperactivity must often be resolved using an anterior deprogrammer, leaf gauge, or Lucia jig. Once the masticatory muscles release their habitual memory, the clinician records an accurate CR bite record at the proposed therapeutic vertical height.
Restorative Space Assessment and Tooth Prognosis
A primary clinical challenge in full-mouth rehabilitation is managing limited restorative space. Clinicians must assess whether there is adequate clearance between arches to deliver materials—such as high-strength monolithic zirconia or lithium disilicate—with sufficient thickness to resist structural fracture.
Simultaneously, every individual tooth must undergo a comprehensive prognostic evaluation, considering:
- Remaining Ferrule: A minimum of 1.5 to 2 millimeters of healthy tooth structure above the bone margin is necessary to secure a lasting crown without biological failure.
- Crown-to-Root Ratio: Severe wear often leaves a short clinical crown with an unfavorable biomechanical lever arm.
- Periodontal Architecture: Bone levels, tooth mobility, and furcation involvements determine whether a tooth is maintainable over the long term.
- Strategic Extraction vs. Retention: If a tooth’s structural compromise puts the entire restorative arch at risk, planned extraction and replacement with dental implants may offer a more predictable long-term foundation.
By mapping out the interface between natural dentition and strategic implant placement, a comprehensive oral reconstruction plan ensures no single restorative unit is overburdened.
The Step-by-Step Architecture of Vertical Dimension Management
Modifying a bite requires careful adherence to an orderly sequence of biological, mechanical, and aesthetic planning steps.
1. Establishing Incisal Edge Position
Planning does not begin at the back of the mouth; it begins with the incisal edge of the maxillary central incisors. The clinician evaluates how much incisal tooth structure should be visible at rest (typically 1 to 3 millimeters depending on age, sex, and lip length) and during an unforced, dynamic smile. The position of these edges establishes the aesthetic horizon and serves as the baseline for the entire reconstructive plane.
2. The Diagnostic Wax-Up (Analog or Virtual)
Once the maxillary incisal edge is determined, the prosthodontist, working with advanced dental laboratory technicians, creates an anatomical diagnostic wax-up. This wax-up models the intended shape, contour, length, and occlusal anatomy of every tooth at the newly established VDO. It establishes the planned anterior guidance (how front teeth disengage back teeth during jaw movement) and ensures even, bilateral contacts across all posterior units.
3. Treatment Sequencing and Staging
A full-arch or dual-arch reconstruction cannot be completed simultaneously without meticulous staging. As detailed in our guide to treatment sequencing in complex reconstructions, procedures are separated into logical phases:
- Disease control (periodontal stabilization, caries management).
- Surgical and implant placement, if indicated.
- Provisional stabilization of vertical dimension.
- Definitive segment-by-segment or arch-by-arch restoration.
The Provisional Phase: "Test Driving" the New Vertical Dimension
No full-mouth rehabilitation should move directly from diagnostic wax-up to permanent ceramic restorations. The human neuromuscular system is highly sensitive to altered occlusal contacts. The transitional phase—utilizing fixed, laboratory-fabricated provisional restorations—is the most critical checkpoint in vertical dimension management.
The provisional restorations directly duplicate the diagnostic wax-up, locking in the planned VDO, anterior guidance, and aesthetic contours. Patients typically wear these high-density provisional restorations for a minimum of eight to twelve weeks. This period serves several vital clinical functions:
Neuromuscular and TMJ Adaptation
The masticatory muscles (masseter, temporalis, medial and lateral pterygoids) must adjust their resting muscle spindle lengths to the newly created vertical dimension. During this adaptation phase, the patient is carefully monitored for any signs of muscular tenderness, jaw fatigue, joint clicking, or headache symptoms. If discomfort occurs, minor occlusal adjustments can be made directly to the provisional material to identify the issue before ceramic work begins.
Phonetic Evaluation
Speech patterns provide a precise, objective verification of vertical dimension. During the provisional trial, clinicians evaluate:
- The Closest Speaking Space: When pronouncing sibilant sounds ("sixty-six," "Mississippi"), the incisal edges of the maxillary and mandibular teeth should approach each other without clicking or clashing, preserving a 1 to 1.5-millimeter space.
- "F" and "V" Sounds: Produced when the incisal edges of the upper teeth gently contact the wet-dry line of the lower lip, verifying appropriate incisal length.
Aesthetic and Occlusal Refinement
The provisional phase allows the patient to evaluate the appearance, lip support, and chewing function of their new teeth in everyday life. Clinicians assess mutual protection: when the patient closes straight down, posterior teeth contact with equal, simultaneous axial force while anterior teeth hold slightly lighter contacts. When the jaw moves forward or sideways, the anterior teeth smoothly separate the posterior teeth (disclusion), preventing damaging lateral forces on back teeth and implants.
Once comfort, function, and aesthetics are completely stable and confirmed over several weeks, the provisional contours are captured via cross-mounting impressions to guide the fabrication of the definitive restorations with absolute fidelity.
Definitive Reconstruction: Material Science and Maintenance
Moving from provisional to definitive restorations involves precise material engineering. Different dental materials interact uniquely with dynamic bite forces:
- Monolithic Zirconia: Exceptionally durable against catastrophic fracture, making it an ideal choice for posterior full-coverage crowns and full-arch implant bridges in patients with a history of severe bruxism. Proper polishing of zirconia is essential to minimize wear on opposing enamel.
- Lithium Disilicate (Glass Ceramic): Offers superior optical translucency and can be reliably bonded to remaining enamel and dentin. It is frequently indicated for anterior crowns, veneers, and conservative onlays where natural aesthetic integration is paramount.
- High-Noble Metal-Ceramics: A proven, classic option providing precise marginal fit and predictable wear compatibility against opposing natural dentition.
Long-Term Maintenance and Bite Protection
Completing a full-mouth rehabilitation is a substantial investment in overall oral health, but it does not make the mouth invulnerable to mechanical forces. Parafunctional grinding habits that originally caused bite collapse often persist on a central neurological level.
To protect new restorations against nocturnal bruxism, a custom-fitted occlusal guard (night guard) is typically prescribed. Fabricated from a hard, flat-plane acrylic, the guard distributes nightly bite forces evenly, maintains the established vertical dimension, and shields both the ceramic margins and underlying implant fixtures from undue torque.
Prosthodontic Care at Nova Premier Dental
Because vertical dimension management involves redefining the structural, mechanical, and aesthetic foundation of the entire oral cavity, it demands advanced clinical expertise. A general dentist often focuses on restoring individual teeth as problems arise, but managing comprehensive rehabilitations requires deep training in occlusal theory, biomaterials, and complex jaw dynamics.
Dr. Peterson Huang is a dual board-certified prosthodontist who completed years of specialized, post-doctoral training dedicated exclusively to complex oral reconstruction, dental implants, and full-mouth bite rehabilitation. As an active member of the prosthodontic community, Dr. Huang approaches vertical dimension management not with guesswork, but through methodical, evidence-based planning tailored to each patient's individual anatomical profile.
For patients facing severe wear, missing teeth, or bite-related discomfort throughout Falls Church, McLean, Great Falls, Arlington, and the broader Northern Virginia region, receiving care from a specialist ensures that your treatment plan is structured for long-term physiological stability.
Navigating comprehensive dental reconstructions also requires practical planning. Nova Premier Dental offers in-house payment plans for qualifying patients, allowing treatment costs to be paid over several months while patients enjoy their new smile.
Summary: The Path to a Reconstructed Bite
| Phase | Clinical Objectives | Patient Benefit |
|---|---|---|
| 1. Diagnostic Blueprint | CBCT, facebow transfer, establishing Centric Relation, diagnostic wax-up. | Ensures predictable, personalized planning based on anatomy rather than arbitrary standards. |
| 2. Space Assessment & Prognosis | Evaluating ferrule, remaining dentin, and strategic implant integration. | Prevents biological failures and saves restorable natural teeth wherever feasible. |
| 3. Provisional Trial | Fixed temporaries worn for 8–12 weeks; testing speech, chewing, and muscle comfort. | Allows patients to "test drive" their new bite and appearance before definitive ceramics are made. |
| 4. Definitive Reconstruction | Precision laboratory fabrication of zirconia, lithium disilicate, or implant prostheses. | Delivers lasting structural stability, restored chewing function, and natural facial harmony. |
If you are experiencing worn down teeth, chronic bite instability, or changes in your facial profile, specialized evaluation can clarify whether your vertical dimension has collapsed and guide you toward a structured, predictable solution. Learn more about our prosthodontic specialty care in Northern Virginia or schedule a consultation with our clinical team at Nova Premier Dental in Falls Church.
Disclaimer
The information provided on this website and blog is intended for general educational and informational purposes only and should not be considered dental or medical advice, diagnosis, or treatment. Reading content on this website does not establish a doctor-patient relationship with Nova Premier Dental or Dr. Peterson Huang. Dental conditions and treatment needs vary from patient to patient. Individuals should consult directly with a qualified dental professional for personalized evaluation, diagnosis, and treatment recommendations. Do not delay seeking professional dental care based on information found on this website. While we strive to provide accurate and up-to-date information, no guarantee is made regarding the completeness, accuracy, or applicability of the content. Treatment outcomes may vary depending on individual circumstances. If you are experiencing a dental emergency or urgent oral health concern, please contact a licensed dental professional immediately or call 911 in the event of a medical emergency.


